
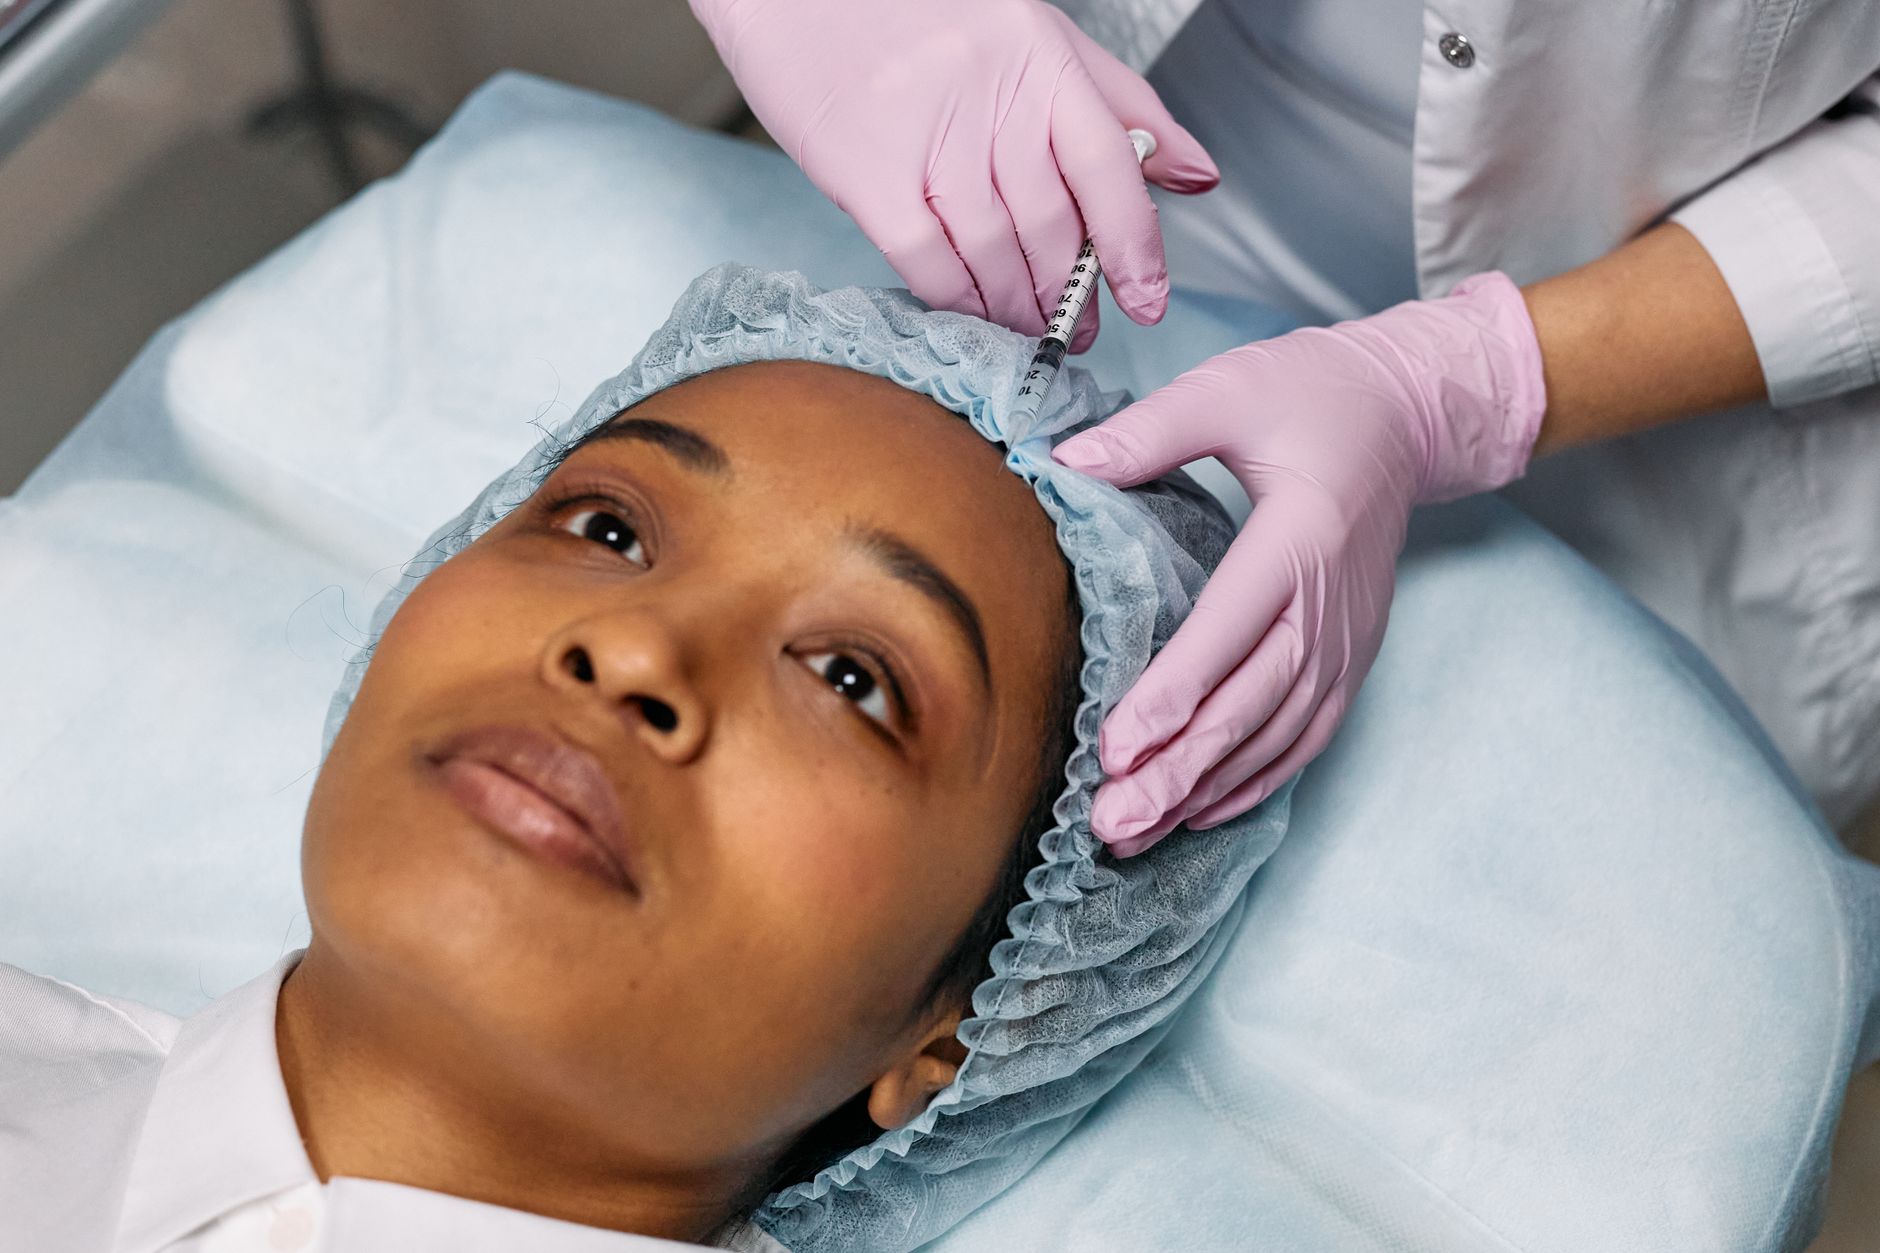
Facial aging changes the way light hits the skin. Shadows pool beneath the eyes, cheekbones lose their high structural ground, and the jawline blurs into the neck. These shifts happen because bone resorption and fat pad deflation alter the architecture underneath the surface. Fixing these changes requires more than putting product wherever a shadow appears. Practitioners approach facial rejuvenation by looking at how different layers of the face interact with age. Treating the face as a single uniform canvas leads to heavy results. Every region demands a specific material property and placement depth. A product placed deep against the bone needs to withstand heavy mechanical stress, while material placed right beneath the skin must remain soft and fluid. Understanding these mechanical needs guides how specialists choose and layer injectable fillers.
Volume restoration starts at the midface because the upper and lower cheeks act as the primary support pillars for the lower face. When the deep fat pads in the cheek area deflate, everything above them sags downward. Restoring cheek volume requires a robust product with high G-prime, which is a measure of a gel's firmness and resistance to deformation. High G-prime gels stay where they are put and push the skin outward, recreating the youthful projection of the cheekbones. Cheek augmentation relies on deep supraperiosteal placement. Depositing material directly on top of the bone mimics natural skeletal support. A 2018 clinical review published in dermatologic literature noted that deep bolus injections in the midface reduce the total volume needed compared to superficial threading, because foundational support lifts the overlying tissue. This structural lift naturally softens folds around the nose and mouth without needing direct product placement in those creases.
Table of Contents
Selecting Medical Materials for Structural Support
Practitioners frequently evaluate different viscosity levels for specific tissue planes when working with dermal fillers. Professionals sourcing these materials benefit from reviewing professional dermal fillers ordering options to secure formulations tailored for deep structural support versus superficial correction. These supply catalogs provide access to high-density HA filler options designed specifically for structural cheek augmentation. Selecting the right medical-grade dermal fillers ensures that practitioners have access to safe, reliable products for complex structural work across various facial zones. High-density hyaluronic acid formulations are manufactured through advanced cross-linking processes that slow enzymatic degradation, allowing the material to maintain its structural integrity under the constant mechanical strain of facial animation.
Complex structural correction demands a thorough understanding of facial fat compartments and muscular attachments. The superficial fat layers slide independently over the deep compartments, creating unique vectors of movement during animation. Injectors must respect these gliding planes to prevent the product from shifting or restricting natural expression. Choosing appropriate dermal fillers for each specific depth prevents long-term complications like product migration or chronic edema. Superficial planes require low-density products that integrate with thin dermal tissue, while deep planes require high-cohesivity gels that can resist compressive muscular forces.
Navigating the Delicate Periorbital Zone
Moving higher toward the eyes reveals a completely different anatomical challenge. The skin here is paper-thin, and the underlying muscle sits very close to the surface. Treating tear trough hollowing requires a delicate touch and a completely different material profile than the cheeks. A firm gel placed under the eye will create lumps, bluish discoloration known as the Tyndall effect, or chronic swelling. Under eye filler must have low water-binding capacity and low G-prime. Hyaluronic acid filler used in this area should integrate smoothly into the tissue without drawing excess fluid from the surrounding skin. Placement happens deep to the orbicularis oculi muscle, right against the orbital bone, to avoid surface irregularities. Even when placed correctly, the margin for error is narrow. Tear trough filler demands precise micro-droplet techniques to smooth the transition between the lower eyelid and the cheek without creating puffiness.
Clinical protocols emphasize the importance of aspiration before product deposition, particularly in vascular-dense regions like the temple, tear trough, and nasal dorsum. Anatomical variations mean that safe injection boundaries shift slightly between different patients. Detailed topographical knowledge remains the primary safeguard against vascular occlusion. Practitioners rely on blunt-tip cannulas in high-risk zones to reduce the likelihood of vessel perforation, reserving sharp needles primarily for precise supraperiosteal placement where deep bone contact provides stability.
Defining the Lower Face and Jawline
The lower third of the face faces constant dynamic movement from chewing, talking, and smiling. Jawline contouring requires a balance between firmness and flexibility. If the material is too soft, the strong pull of the platysma and masseter muscles will flatten it. If it is too rigid, the jawline will look blocky and unnatural when the face moves. Achieving a sharp non-surgical facelift along the mandible involves layered injection strategies. Deep boluses anchor the angles of the jaw, while linear threading along the body of the mandible creates a sharp border. This combination of deep structural placement and superficial refinement addresses both bone loss and skin laxity. Injectable fillers used here need to mimic the density of natural mandibular bone while remaining pliable enough to move with the facial muscles.
Histological studies show that hyaluronic acid undergoes slow enzymatic degradation over time, stimulating localized neocollagenesis as the gel integrates with the extracellular matrix. This tissue response means that successive treatments often require less total volume than the initial correction. The structural scaffolding laid down during the first session alters the local tissue environment, promoting a firmer baseline structure even after partial product resorption. Long-term management of facial aging relies on maintaining this structural baseline rather than chasing complete deflation with large, isolated boluses.
The Logic of Layered Integration
The secret to modern facial aesthetics lies in combining these approaches rather than relying on a single injection site. A layered filler technique uses different densities of hyaluronic acid across multiple tissue depths in the same session. Deep layers receive high-G-prime gels for structural support, middle layers receive moderate gels for contouring, and superficial layers receive soft gels for fine lines. Patient anatomy dictates every choice in this process. Facial contouring is never one-size-fits-all, because bone structure, skin thickness, and fat distribution vary wildly from person to person. Clinical success depends on matching the rheological properties of the product to the mechanical demands of the target zone. Careful mapping ensures that midface volume loss and jawline degradation are corrected in harmony, restoring balance to the entire facial structure.
Patient consultation protocols require a detailed assessment of previous treatments, skin thickness, and dynamic facial animation. Static evaluation fails to capture how dermal fillers behave under the strain of daily expression. Observing the face in motion helps practitioners place product where it supports structural integrity without creating abnormal mechanical resistance. Careful planning transforms temporary volume correction into a cohesive structural strategy that ages gracefully alongside the patient.
1 thought on “Layered Rejuvenation: Strategic Selection of Dermal Fillers for Tear Troughs, Chews, and Jawlines”